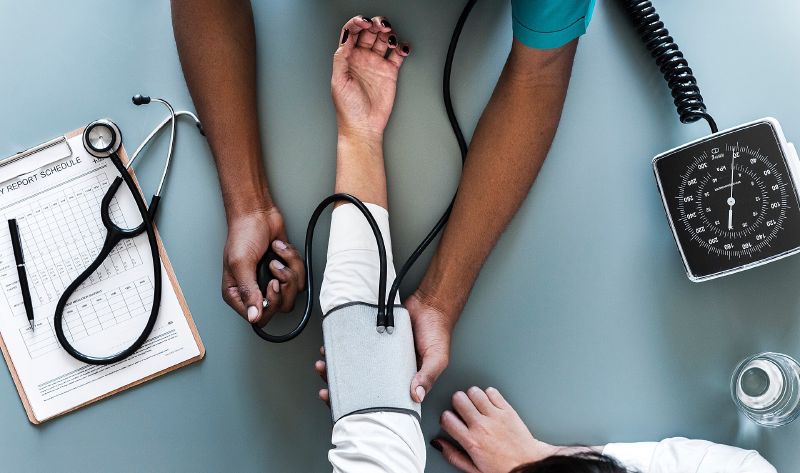
Which arm you use barely changes a blood pressure reading. How you hold that arm changes it a great deal. A Johns Hopkins Medicine trial compared an arm hanging unsupported at the side with one resting on a desk at heart level. The hanging arm pushed the systolic number up by 6.5 mmHg on average and the diastolic number up by 4.4 mmHg. Swap arms instead of positions, and Harvard Health puts the usual left-right gap at 5 mmHg systolic or less.
So “which arm” really has two answers, and they carry different weight.
Left arm or right?
The Cleveland Clinic says either arm will do for a reading. The Rotherham NHS Foundation Trust, which lends monitors to patients, tells them to cuff the left arm unless a clinician has said otherwise. These are not contradictions so much as answers to slightly different questions: which arm suffices for a one-off reading, and which arm a service defaults to when it hands out equipment.
What the sources agree on is consistency. Harvard recommends measuring both arms at least once, because one arm, usually the right, tends to read a little higher. Once you know which, use that same arm every time afterwards. Alternating between the two from one reading to the next can look like your blood pressure has changed when only the arm has.
There is a clinical reason to check both arms beyond consistency, not just a practical one. Guidelines call for measuring both partly to catch a gap that can point to narrowed blood vessels, such as subclavian artery stenosis or aortic coarctation, according to a review in the Korean Circulation Journal. Harvard sets its own threshold for concern at a systolic gap of more than 10 mmHg, held consistently rather than seen once, and says to mention it to a doctor. The review cites a stricter cut-off of more than 20 mmHg used in vascular research that takes both arms at the same time rather than one after the other. The two figures answer different questions. One is an everyday prompt to see a doctor, and the other is a threshold from vascular screening research.
Where the larger difference comes from
Arm position is a separate question, and the numbers involved are bigger. Tammy Brady is a paediatrics professor at Johns Hopkins and the trial’s senior author. She and her team tested 133 adults, average age 57, in three positions: arm resting on a desk at heart level, resting in the lap, and hanging unsupported at the side. Lap support overestimated the systolic reading by 3.9 mmHg and the diastolic reading by 4 mmHg, against the desk position. The unsupported position pushed the systolic reading up by about 6.5 mmHg and the diastolic reading up by about 4.4 mmHg, on average. Among people whose blood pressure already ran high, the gap for an unsupported arm widened to 8.5 mmHg systolic.
That gap can move someone across a diagnostic line. NPR gave the example of a patient with a systolic reading of 128 mmHg, in the elevated range, whose number a dangling arm could push above 130, and into the range NPR called solidly hypertensive. Working from the US Centers for Disease Control and Prevention’s National Health and Nutrition Examination Survey, the researchers behind the trial went further: if arm position were always wrong, they estimated it would wrongly classify 16 per cent of US adults, around 40 million people, as hypertensive.
Guidelines already called for the arm to rest supported. The British and Irish Hypertension Society calls for it “supported at the level of the heart”, NICE wants it “outstretched and supported”, and the CDC specifies an arm resting on a table at chest height. The trial did not change that advice. It measured how much difference ignoring it makes.
Why the wrong position persists
Stephen Juraschek directs the Hypertension Center at Beth Israel Deaconess Medical Center in Boston. He told NPR that clinics have known the guidance for years, yet doing it “in a real-world setting has been tricky.” In his experience the errors tend to cluster, so a dangling arm is rarely the only thing wrong with how a reading is taken, and he has seen a “net reduction of like 20 mmHg” once several small mistakes stack up.
Part of the problem is the room. Exam tables often have nowhere to rest an arm at heart height, and Brady said she rearranges furniture before seeing patients to get the position right.
What the trial does not settle
The trial’s own limits are worth naming. It included 133 people, 77 per cent of them Black and 53 per cent women, so the size of the effect may not carry over to other groups in the same proportions. It also measured how large the effect is rather than how often clinics get the position wrong in practice. The researchers wrote only that “proper arm position is commonly overlooked.” UK coverage of the study, the British Heart Foundation noted, left out that the desk in the trial sat at heart level, which is the detail the whole result depends on.
The version you can act on
Rest your arm on a table so your elbow sits level with your heart, not in your lap and not hanging by your side. Use the same arm every time you measure, having checked both once to see if one runs higher. Sit with your feet flat on the floor, your back supported, and rest quietly for five minutes before the cuff inflates. Get those three things right, and the arm you pick is the smallest decision left to make.